
Chronic lower back pain can come from several different structures, including spinal discs, nerves, muscles, the sacroiliac joints, and the small joints along the back of the lumbar spine known as the facet joints.
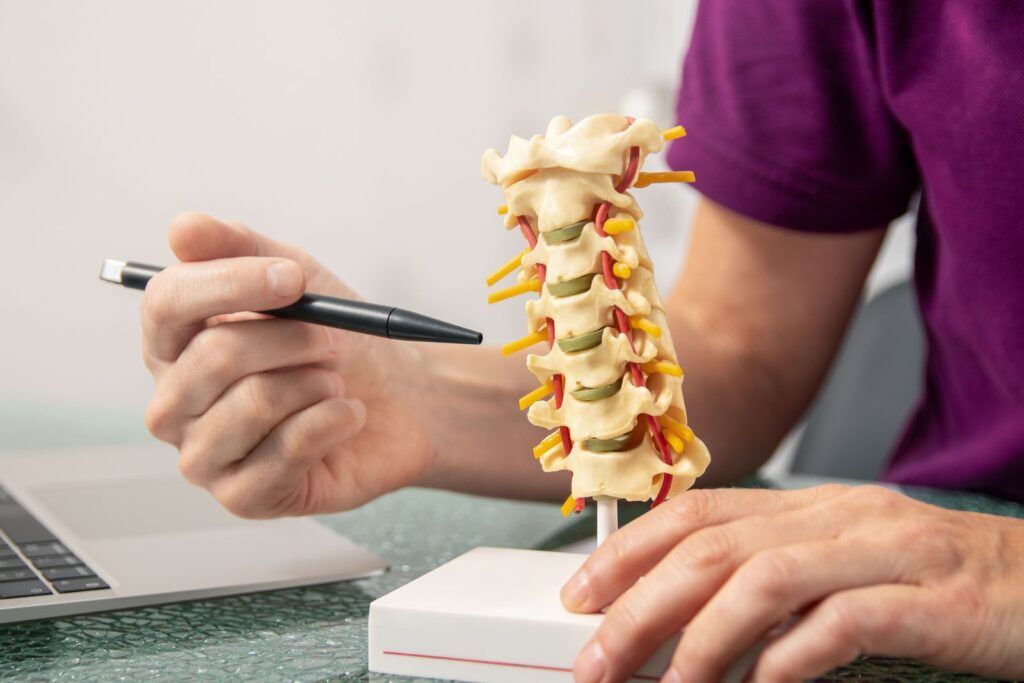
When the lumbar facet joints are suspected as the source of pain, a lumbar medial branch block can help determine whether they are contributing to a patient’s symptoms.
A lumbar medial branch block is a targeted diagnostic procedure that temporarily numbs the small medial branch nervesthat carry pain signals from the lumbar facet joints.
If temporarily blocking these nerves produces meaningful relief of the patient’s typical lower back pain, the response can provide important diagnostic information and help determine whether lumbar radiofrequency ablation (RFA) may be an appropriate next step.
At TOPS Institute, we provide image-guided lumbar medial branch blocks in Los Angeles and Beverly Hills as part of a diagnosis-driven approach to chronic low back pain.
A lumbar medial branch block is a diagnostic injection used to determine whether pain is originating from one or more facet joints in the lower spine.
The lumbar facet joints are small paired joints located along the back of the spine.
These joints receive sensory innervation from small nerves called medial branch nerves.
During a medial branch block, a small amount of local anesthetic is carefully placed near selected medial branch nerves.
The medication temporarily interrupts pain signals traveling from the suspected facet joints.
The patient’s response to the block can help determine whether those joints are contributing to chronic lower back pain.
The medial branch nerves are small sensory nerves that carry pain signals from the lumbar facet joints.
If a facet joint becomes painful because of arthritis, degeneration, injury, or mechanical stress, these nerves can transmit pain signals to the central nervous system.
By temporarily numbing selected medial branch nerves, the physician can evaluate whether the corresponding facet joints are significant pain generators.
If the patient’s usual pain improves during the expected period of anesthetic effect, this supports the diagnosis of facet-mediated low back pain.
Lumbar medial branch blocks may be considered when symptoms suggest that the lumbar facet joints are contributing to chronic pain.
Potential conditions and clinical situations include:
The procedure is not intended to diagnose every type of back pain.
It specifically evaluates pain transmitted from the lumbar facet joints through the medial branch nerves.
Lumbar spondylosis, commonly referred to as back arthritis, involves degenerative changes within the lower spine.
These changes may affect:
When the facet joints become painful, patients may experience aching lower back pain, stiffness, reduced mobility, and discomfort with certain movements.
A lumbar medial branch block may help determine whether the facet joints are responsible for those symptoms.
The procedure does not reverse arthritis. Its role is to provide diagnostic information that can guide treatment.
Facet-mediated lower back pain can vary, but common symptoms may include:
Facet-mediated pain is often described as axial low back pain, meaning the discomfort is centered primarily in the spine rather than traveling down the leg along a nerve.
Distinguishing facet-mediated pain from lumbar radiculopathy or sciatica is important because the treatment pathways are different.
Common features may include:
Common features may include:
Sciatica typically involves irritation or compression of a spinal nerve root.
A lumbar medial branch block does not test or treat the spinal nerve roots responsible for radiculopathy.
Lumbar medial branch blocks are generally performed as outpatient procedures using image guidance.
The procedure typically involves:
Because the goal is diagnostic precision, the amount of anesthetic used around each nerve is typically limited.
The hours after the procedure are an important part of the diagnostic process.
Patients may be asked to monitor:
For example, if standing or extending the lower back typically causes pain, the patient may be asked to observe whether that movement becomes more comfortable while the anesthetic is active.
Documenting these changes can help the physician interpret the results.
A diagnostic medial branch block is intended to provide temporary pain relief.
The duration depends on the local anesthetic used.
The goal is not to provide long-term treatment.
Instead, the temporary response helps determine whether the targeted facet joints are contributing to the patient’s pain.
If the pain returns after the anesthetic wears off, that does not necessarily mean the procedure was unsuccessful.
The key information is how much the patient’s typical pain improved while the block was active.
A lumbar medial branch block may be considered diagnostically supportive when the patient experiences the expected degree of temporary relief of their typical pain.
The physician may consider:
Specific criteria may vary depending on clinical guidelines and insurance requirements.
The response should therefore be interpreted within the context of the patient’s overall clinical presentation.
Some patients may undergo more than one diagnostic medial branch block before lumbar radiofrequency ablation is considered.
The appropriate protocol may depend on:
The purpose of repeated diagnostic testing is to increase confidence that the facet joints are truly responsible for the patient’s pain before proceeding with a longer-lasting nerve treatment.
These procedures both relate to the lumbar facet joints but target different structures.
A medial branch block places local anesthetic near the nerves that transmit pain signals from the facet joints.
Its primary purpose is diagnostic, especially when radiofrequency ablation is being considered.
A lumbar facet joint injection places medication directly inside the facet joint.
It may be used in selected patients to address pain or inflammation associated with the joint.
These procedures treat different pain mechanisms.
A lumbar medial branch block evaluates facet-mediated back pain.
A lumbar epidural steroid injection targets inflammation around spinal nerve roots and is more commonly used for radicular symptoms such as sciatica.
One of the most important roles of a lumbar medial branch block is determining whether a patient may benefit from lumbar radiofrequency ablation.
A typical treatment pathway may look like:
Suspected Lumbar Facet Joint Pain
↓
Lumbar Medial Branch Block
↓
Temporary Relief of Typical Pain
↓
Confirm Facet-Mediated Pain
↓
Lumbar Radiofrequency Ablation for Appropriately Selected Patients
Radiofrequency ablation uses controlled radiofrequency energy to disrupt selected medial branch nerves that transmit pain signals from the painful facet joints.
Because the nerves can regenerate over time, the effects are not necessarily permanent.
However, RFA may provide longer-lasting relief than the temporary anesthetic effect of a diagnostic block.
A lumbar medial branch block may be considered when chronic lower back pain appears to originate from the facet joints.
Potential candidates may include patients who:
The patient’s history, physical examination, imaging when appropriate, and previous treatment all contribute to the decision.
Not all low back pain is facet-mediated.
If symptoms are caused primarily by lumbar radiculopathy or sciatica, treatment directed toward the affected spinal nerve may be more appropriate.
If pain is primarily caused by the sacroiliac joint, a different diagnostic and treatment pathway may be required.
Other potential pain generators include discs, muscles, spinal stenosis, and other musculoskeletal structures.
The treatment should follow the diagnosis.
Lumbar medial branch blocks are minimally invasive procedures, but all injections have potential risks.
Potential risks and side effects may include:
Patients taking blood-thinning medications or those with certain medical conditions may require additional planning before treatment.
The potential benefits, risks, and alternatives should be reviewed individually.
Lumbar medial branch blocks are generally outpatient procedures.
Patients are usually monitored briefly after treatment and receive instructions regarding activity.
Because the procedure is diagnostic, patients may be asked to carefully track their pain and function during the hours following the injection.
A pain diary can be useful for recording:
This information may help determine the next step in treatment.
Chronic low back pain cannot always be accurately diagnosed from an MRI or X-ray alone.
At TOPS Institute, we take a diagnosis-driven approach to lumbar facet pain.
We evaluate:
When the lumbar facet joints are suspected as a significant pain source, a medial branch block can provide valuable diagnostic information.
For patients who experience an appropriate response to diagnostic blocks, lumbar radiofrequency ablation may then be considered for longer-lasting pain management.
For patients seeking lumbar medial branch blocks in Los Angeles or Beverly Hills, TOPS Institute provides personalized interventional pain management focused on identifying the pain generator before proceeding with treatment.
A lumbar medial branch block is a diagnostic procedure in which local anesthetic is placed near the small nerves that carry pain signals from the lumbar facet joints.
It helps determine whether one or more lumbar facet joints are contributing to chronic lower back pain.
It is primarily a diagnostic test. Temporary pain relief may occur, but the main purpose is to determine whether the facet joints are the source of pain and whether radiofrequency ablation may be appropriate.
The anesthetic effect is temporary and generally lasts according to the medication used. The short duration is expected and provides diagnostic information.
If the patient experiences the expected degree of temporary pain relief, it may indicate that the targeted facet joints contribute to the pain. Depending on clinical guidelines and individual circumstances, another block or lumbar radiofrequency ablation may be considered.
Some patients may undergo more than one diagnostic block before RFA. The protocol depends on clinical guidelines, individual response, and insurance requirements.
A medial branch block targets the nerves that carry pain signals from the facet joints. A facet joint injection places medication directly inside the joint.
A medial branch block evaluates facet-mediated back pain. An epidural steroid injection targets inflammation around spinal nerve roots and is generally used for radicular symptoms such as sciatica.
They are not designed to treat classic sciatica caused by nerve-root irritation. If leg pain is caused by lumbar radiculopathy, an epidural or another nerve-targeted treatment may be more appropriate.
For appropriately selected patients whose diagnostic blocks support facet-mediated pain, lumbar radiofrequency ablation may be considered to provide longer-lasting reduction in pain signals from the affected joints.
Persistent lower back pain can originate from many different structures, and imaging alone may not identify which one is actually responsible.
A lumbar medial branch block can help determine whether the facet joints are contributing to your pain and whether a longer-lasting treatment such as radiofrequency ablation may be appropriate.
Schedule a consultation with TOPS Institute in Los Angeles or Beverly Hills for evaluation of chronic low back pain and suspected lumbar facet-mediated pain.
Schedule an Appointment
Leave a message or give us a call — we'll find a time that works for you.
640 South San Vicente Blvd., Suite 389, Los Angeles, CA 90048

Interventional pain management for Los Angeles & Beverly Hills — image-guided care that treats the source, not just the symptom.
© 2026 TOPS Institute · All rights reserved · Home