
Chronic lower back pain can originate from several different structures. For some patients, the source is the small joints along the back of the lumbar spine known as the facet joints.
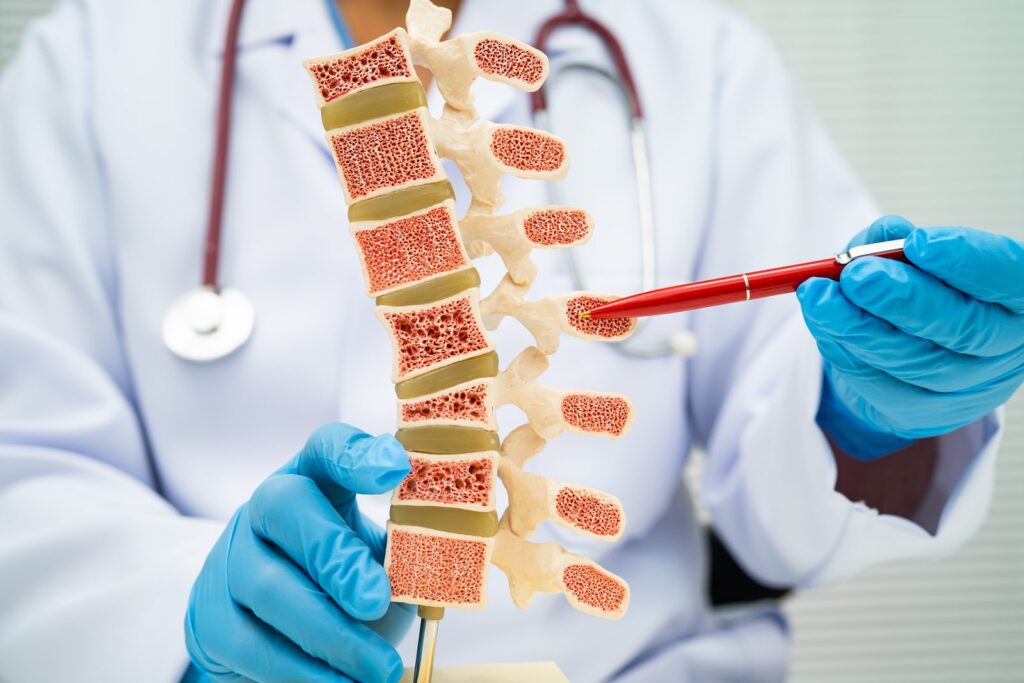
When diagnostic lumbar medial branch blocks confirm that the facet joints are contributing to pain, lumbar radiofrequency ablation (RFA) may be considered to provide longer-lasting relief.
Lumbar radiofrequency ablation is a minimally invasive procedure that uses controlled radiofrequency energy to disrupt selected medial branch nerves responsible for transmitting pain signals from the lumbar facet joints.
At TOPS Institute, we provide image-guided lumbar radiofrequency ablation in Los Angeles and Beverly Hills as part of a diagnosis-driven approach to chronic low back pain. By confirming the pain source before treatment, we can determine whether lumbar RFA is appropriate for each patient.
Lumbar radiofrequency ablation is a minimally invasive procedure that uses controlled radiofrequency energy to reduce pain signals transmitted by selected medial branch nerves associated with the facet joints of the lower spine.
The lumbar facet joints are paired joints located along the back of the spine. They help provide stability while allowing controlled movement.
Small nerves known as medial branch nerves transmit pain signals from these joints.
During lumbar RFA, a specialized needle is positioned near the appropriate medial branch nerve. Controlled radiofrequency energy creates a targeted thermal lesion that reduces the nerve’s ability to transmit pain.
The procedure is also sometimes referred to as:
Lumbar RFA does not remove the facet joint or reverse arthritis. Its purpose is to reduce pain transmission from a confirmed facet pain source.
Lumbar RFA is primarily used for chronic facet-mediated lower back pain.
It may be considered for selected patients with:
Patients may experience symptoms such as:
Lumbar RFA is not a universal treatment for lower back pain. Determining whether the facet joints are responsible is an important part of patient selection.
Lumbar spondylosis, commonly referred to as back arthritis, involves degenerative changes within the lumbar spine.
These changes may affect the:
When degeneration affects the facet joints and those joints become painful, patients may develop persistent axial lower back pain.
Lumbar radiofrequency ablation does not repair arthritis, regenerate cartilage, or reverse structural degeneration.
Instead, it targets the medial branch nerves responsible for carrying pain signals from the affected facet joints.
For appropriately selected patients, reducing these pain signals may improve comfort, mobility, and function.
Diagnostic lumbar medial branch blocks are an important part of determining whether a patient may benefit from lumbar RFA.
A typical pathway is:
Suspected Lumbar Facet Joint Pain
↓
Diagnostic Lumbar Medial Branch Block
↓
Meaningful Temporary Relief of Typical Pain
↓
Evidence Supporting Facet-Mediated Pain
↓
Lumbar Radiofrequency Ablation for an Appropriate Candidate
During a medial branch block, local anesthetic is placed near the nerves carrying pain signals from the suspected facet joints.
If temporarily numbing these nerves produces the expected improvement in the patient’s typical pain, the response provides evidence that the corresponding facet joints may be significant pain generators.
Specific criteria for proceeding to RFA can vary according to clinical guidelines and insurance requirements.
Radiofrequency ablation uses electrical energy to generate controlled heat at the tip of a specialized needle.
The physician positions the needle near a selected medial branch nerve.
Radiofrequency energy is then delivered to create a controlled lesion in the targeted nerve.
This interrupts the nerve’s ability to transmit pain signals from the facet joint toward the central nervous system.
Importantly, RFA does not permanently remove the nerve.
Medial branch nerves can regenerate over time, which is one reason pain may eventually return after a period of improvement.
Lumbar RFA is generally performed as an outpatient procedure using image guidance.
The procedure typically involves:
The specific levels treated depend on which facet joints have been identified as contributing to the patient’s pain.
The medial branch nerves are small and follow predictable anatomical pathways near the vertebrae.
Image guidance allows the physician to accurately identify relevant spinal anatomy and position the radiofrequency needles near the intended nerve targets.
Because the goal is to treat selected medial branch nerves rather than surrounding tissues, accurate needle positioning is an important part of the procedure.
A lumbar medial branch block and lumbar radiofrequency ablation target the same general nerves but serve different purposes.
A medial branch block uses local anesthetic to temporarily numb the nerve.
Its primary purpose is diagnostic—to determine whether the corresponding facet joints are contributing to the patient’s pain.
RFA uses controlled radiofrequency energy to create a lesion in the targeted nerve and provide a longer-lasting interruption of pain transmission.
In many patients, the medial branch block comes first and RFA is considered only if the diagnostic response supports facet-mediated pain.
These procedures are also different.
A facet joint injection places medication directly into the joint.
RFA targets the medial branch nerves that carry pain signals from the joint.
Facet joint injections may be considered in selected circumstances, while medial branch blocks and RFA form a separate diagnostic and therapeutic pathway for confirmed facet-mediated pain.
One of the most important distinctions for patients is the difference between facet-mediated back pain and sciatica.
Lumbar RFA targets medial branch nerves associated with the facet joints.
It is primarily used for chronic axial low back pain arising from these joints.
An epidural steroid injection delivers anti-inflammatory medication into the epidural space around spinal nerve roots.
It may be used for conditions such as lumbar radiculopathy and sciatica.
If a patient has shooting or burning pain traveling down the leg because of an irritated spinal nerve, RFA of the lumbar medial branches generally does not address that nerve-root pain.
Lumbar medial branch radiofrequency ablation is not generally used to treat classic sciatica.
Sciatica commonly results from irritation or compression of a lumbar spinal nerve root.
Possible causes include:
Lumbar facet RFA instead targets the medial branch nerves associated with facet-mediated back pain.
Patients with sciatica may require a different treatment approach, such as an epidural steroid injection, depending on the underlying diagnosis.
Lumbar RFA may be considered for patients with chronic lower back pain when diagnostic evaluation supports a facet joint source.
Potential candidates may include patients who:
The presence of facet arthritis on imaging alone does not establish that a patient should undergo RFA.
The patient’s symptoms, examination, and response to diagnostic blocks are important parts of treatment selection.
The duration of pain relief varies from patient to patient.
For appropriately selected patients, improvement may last for several months or longer.
Eventually, the targeted medial branch nerves can regenerate and regain their ability to transmit pain signals.
The underlying arthritis or degeneration may also remain present.
For these reasons, lumbar radiofrequency ablation is not considered a permanent cure.
Yes, repeat lumbar RFA may be considered for selected patients.
If a patient experiences meaningful relief following the initial procedure and the same facet-mediated pain later returns, reevaluation can help determine whether repeating RFA is appropriate.
Factors considered may include:
Repeat RFA should be individualized rather than automatically scheduled.
Pain relief is not always immediate.
Some patients notice improvement relatively soon, while others may require several days or longer before the full benefit becomes apparent.
Temporary soreness or increased discomfort can occur after the procedure.
This does not necessarily indicate that the procedure was unsuccessful.
Patients should follow their physician’s post-procedure instructions and discuss any unexpected or concerning symptoms.
Lumbar radiofrequency ablation is generally performed on an outpatient basis.
Patients may experience:
Specific recommendations regarding driving, exercise, work, and other activities vary depending on the patient and procedure.
Once discomfort improves, patients may be able to participate more comfortably in:
Reducing pain can be particularly valuable when it allows a patient to become more active and improve function.
Lumbar RFA is a minimally invasive procedure, but all medical procedures have potential risks.
Potential risks and side effects may include:
Patients taking blood-thinning medications or those with certain medical conditions may require additional procedural planning.
Potential benefits, risks, and alternatives should be reviewed before treatment.
Lumbar radiofrequency ablation does not remove spinal bones, discs, or facet joints.
The procedure targets selected medial branch nerves responsible for carrying pain signals from the facet joints.
The goal is to reduce pain transmission while preserving the underlying spinal anatomy.
However, as with any interventional procedure, appropriate patient selection and precise technique are important.
Lumbar RFA is specifically intended for appropriately selected patients with facet-mediated pain.
It may not be the appropriate treatment when the primary source of symptoms is:
For example, a patient with sacroiliac joint pain may require an SI joint-directed treatment, while a patient with lumbar radiculopathy may require a nerve-root-directed treatment.
Low back pain is not a single diagnosis.
Pain can originate from the facet joints, spinal nerves, discs, sacroiliac joints, muscles, and other structures.
At TOPS Institute, we take a diagnosis-driven approach to lumbar radiofrequency ablation.
We evaluate:
before determining whether RFA is appropriate.
For patients with confirmed lumbar facet-mediated pain, radiofrequency ablation may provide longer-lasting pain reduction by interrupting pain signals from the affected joints.
For patients seeking lumbar radiofrequency ablation in Los Angeles or Beverly Hills, TOPS Institute provides personalized interventional pain management focused on accurate diagnosis, appropriate patient selection, and targeted treatment.
Lumbar radiofrequency ablation is a minimally invasive procedure that uses controlled radiofrequency energy to reduce pain signals carried by selected medial branch nerves associated with the lumbar facet joints.
Lumbar RFA is primarily used for confirmed facet-mediated lower back pain, including pain associated with lumbar spondylosis and facet arthritis.
It may help selected patients when arthritis or degeneration of the lumbar facet joints is confirmed as a significant source of pain. RFA does not reverse the arthritis itself.
Diagnostic lumbar medial branch blocks are commonly used before RFA to determine whether the facet joints are contributing to the patient’s pain.
Yes. If a patient experienced meaningful benefit and the same facet-mediated pain later returns, repeat RFA may be considered after reevaluation.
The duration varies. Some patients experience meaningful pain reduction for several months or longer. Pain may eventually return as the targeted nerves regenerate.
Lumbar medial branch RFA is generally not used to treat classic sciatica because it targets nerves associated with the facet joints rather than the spinal nerve roots responsible for radicular leg pain.
No. RFA targets medial branch nerves carrying pain signals from the facet joints. Epidural steroid injections deliver medication around spinal nerve roots and are commonly used for radicular pain.
No. A medial branch block temporarily numbs selected nerves for diagnostic purposes. RFA uses controlled radiofrequency energy to produce a longer-lasting interruption of pain transmission.
No. The targeted medial branch nerves can regenerate over time, which is why pain may eventually return.
No. Lumbar RFA is a minimally invasive interventional procedure and does not involve removing spinal tissue or making a traditional surgical incision.
If chronic lower back pain has been traced to the lumbar facet joints and diagnostic medial branch blocks provided meaningful temporary relief, radiofrequency ablation may offer a longer-lasting treatment option.
Schedule a consultation with TOPS Institute in Los Angeles or Beverly Hills to determine whether lumbar radiofrequency ablation may be appropriate for your chronic low back pain, lumbar spondylosis, or facet-mediated pain.
Leave a message or give us a call — we'll find a time that works for you.
640 South San Vicente Blvd., Suite 389, Los Angeles, CA 90048

Interventional pain management for Los Angeles & Beverly Hills — image-guided care that treats the source, not just the symptom.
© 2026 TOPS Institute · All rights reserved · Home